Your immune system ages faster than you do. By your sixties, the cells that once patrolled your body with precision have become sluggish and prone to making mistakes. Now researchers are finding that this immune cell senescence might reshape how your brain functions too. The connection isn’t obvious at first. It takes some unpacking.
What is immune cell ageing
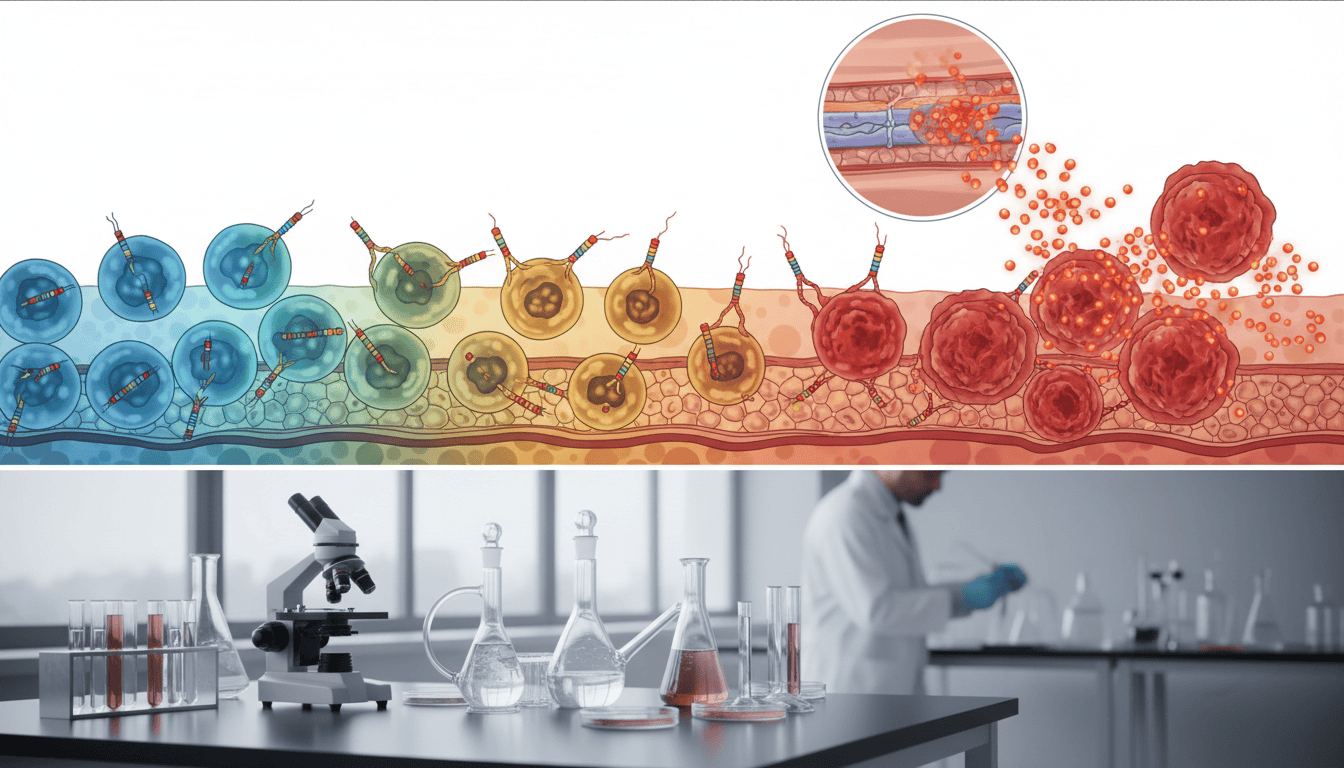
Immune cells, particularly T cells and B cells, have a finite lifespan. Unlike some other cells in your body that divide indefinitely, these defenders can only divide so many times before they hit their limit. This is the Hayflick limit, and it’s real. Each time a cell divides, telomeres on chromosome ends shorten. When telomeres become too short, the cell stops dividing and enters senescence, a state of permanent growth arrest.
But senescent immune cells don’t just sit quietly. They secrete inflammatory molecules called cytokines. Interleukins, TNF-alpha, and other signalling compounds leak into the bloodstream continuously. Think of it as a low-grade alarm that never quite shuts off. This chronic, low-level inflammation is what researchers call “inflammageing.” The immune system becomes less effective at fighting real threats while simultaneously becoming more noisy and irritating to other tissues.
What makes this particularly relevant to cognitive science is that the brain sits behind the blood-brain barrier, a selective filter that keeps most molecules out. But chronic inflammation can compromise this barrier over time. Cytokines and inflammatory proteins find their way through, bathing brain tissue in signals that were meant for peripheral immune responses.
What the research shows
Studies tracking immune cell populations and cognitive performance have revealed a correlation worth taking seriously. Older adults with higher levels of senescent T cells show measurable changes in processing speed and executive function. The association isn’t trivial; some studies find that people with elevated markers of immune senescence perform noticeably worse on cognitive tasks requiring attention or mental flexibility.
In animal models, researchers have demonstrated this more directly. When senescent immune cells accumulate, microglial activation increases in the brain. Microglia are the resident immune cells of the central nervous system, and they respond to peripheral inflammatory signals. Activated microglia prune synapses, the connections between neurons. Too much pruning disrupts memory consolidation and learning efficiency.
The timeline matters. Cognitive changes associated with immune cell senescence emerge gradually, often without obvious symptoms until significant accumulation has occurred. This isn’t like an acute infection where you suddenly feel unwell. It’s more like slow erosion. Brain imaging studies show that people with higher senescent immune cell burden have altered patterns of neural connectivity, particularly in regions associated with memory and attention.
Why cells need this mechanism
The fact that immune cells age at all seems like poor design until you consider the alternative. If immune cells could divide indefinitely, they’d accumulate mutations and potentially become cancerous. The replicative limit is a defence against that risk. Cancer is worse than ageing.
The inflammatory signalling from senescent cells might have once served a purpose too. In younger organisms, it probably signals the immune system to clear out damaged or dysfunctional cells. It’s a cleanup signal. But when senescent cells accumulate faster than the body can remove them, that signal becomes background noise. The system designed for acute communication becomes a source of chronic static.
From an evolutionary standpoint, cognitive maintenance was probably optimised for reproduction and early adulthood. Natural selection doesn’t strongly favour traits that improve thinking in your seventies. The brain’s vulnerability to chronic immune signalling might reflect this historical lack of pressure. Your brain never had to evolve defences against the kind of persistent inflammation that comes with living decades beyond reproductive age.
What affects immune cell ageing
Cytomegalovirus (CMV) infection shapes the composition of your T cell population more than almost anything else. People infected with CMV in childhood, which includes most of the population, carry that virus latently for life. Their immune system dedicates enormous numbers of cells to monitoring CMV, and those cells eventually senesce. CMV-seropositive individuals show accelerated immune ageing compared to the CMV-negative minority.
Physical activity appears to slow immune cell senescence. Aerobic exercise alters T cell dynamics and reduces circulating inflammatory markers. The effect isn’t dramatic, but it’s measurable. Sleep quality matters too. Chronic sleep disruption accelerates senescence in multiple immune populations. Metabolic factors like obesity and poor glucose control correlate with higher senescent cell burden and elevated inflammageing markers.
Psychological stress influences the rate of immune cell ageing. Caregivers under prolonged stress show accelerated telomere shortening in their immune cells. Whether this stress-related immune ageing translates directly to cognitive changes remains an open question, but the biological pathway certainly exists. Genetics play a role as well, with variation in genes affecting telomerase activity and inflammatory response potentially predisposing some people to faster immune ageing than others.
What remains unknown
The causal direction isn’t fully established. Do senescent immune cells cause cognitive changes, or do cognitive changes somehow accelerate immune ageing? Animal models suggest the former, but human studies can only show association. Proving causation in humans would require interventions that specifically clear senescent immune cells and show that cognitive function improves as a result. Such trials are underway, but results take time.
We don’t yet know whether the cognitive effects of immune cell senescence are reversible. Can removing senescent cells restore cognitive function, or is the damage permanent once it’s occurred? The answer probably depends on timing and magnitude. Early intervention might preserve function, while late-stage intervention might only slow further decline.
Individual variation in susceptibility is massive and poorly understood. Some people maintain sharp cognition into their eighties despite high senescent cell burden, while others show cognitive changes much earlier. What protective factors allow some people to resist the cognitive impact of immune cell ageing? Genetic differences, cognitive reserve, physical fitness, and metabolic health all seem involved, but their relative contributions remain unclear.
The mechanisms linking peripheral immune signalling to specific cognitive changes also need clarification. Does inflammageing preferentially affect memory, attention, processing speed, or executive function, or does it degrade cognition more generally? Different studies show different patterns, suggesting either real heterogeneity or methodological variation.
Understanding how immune cell ageing influences cognitive function opens a window onto a biological process that affects most people yet receives little attention in routine medical practice. The immune system ages. That’s unavoidable. But whether that ageing must drag down cognitive function, and at what rate, and whether anything can slow or reverse that process: these are the questions pushing the field forward. The answer likely involves changes to how we think about what it means to age successfully.

Matt Elliott is the editor of Redox News Today, an independent publication covering peer-reviewed research on cellular health, redox signalling, and related biomedical science.